Pharmacist support 24/7

Tecentriq Atezolizumab 1200mg Cancer Immunotherapy Clinical Review and Global Sourcing Guide 2026

Author: Critical Kare PharmaImmuno-Oncology Desk

On October 1, 2026, thoracic and uro-oncology symposiums reiterated the clinical significance of Tecentriq® (Atezolizumab 1200 mg / 20 mL and 840 mg / 14 mL concentrate for solution for infusion) developed by Genentech / Roche. As the first engineered monoclonal antibody targeting programmed death-ligand 1 (PD-L1), Tecentriq reverses T-cell exhaustion while leaving PD-L2 intact, anchoring cornerstone regimens in Extensive-Stage Small Cell Lung Cancer (ES-SCLC), adjuvant non-small cell lung cancer (NSCLC), metastatic urothelial carcinoma, and unresectable hepatocellular carcinoma (HCC).

Through Critical Kare Pharma, verified authentic Genentech / Roche packs of Tecentriq Atezolizumab 1200mg & 840mg Injection are accessible to oncology institutions, clinical research centers, and named patients globally via GDP-certified 2°C–8°C cold-chain logistics and validated Certificate of Analysis (COA) batch release.

Tecentriq Atezolizumab 1200mg vial in sterile oncology cleanroom with digital temperature monitor

Mechanism of Action: Selective PD-L1 Checkpoint Inhibition

Atezolizumab possesses unique molecular design features that differentiate it from other immune checkpoint inhibitors:

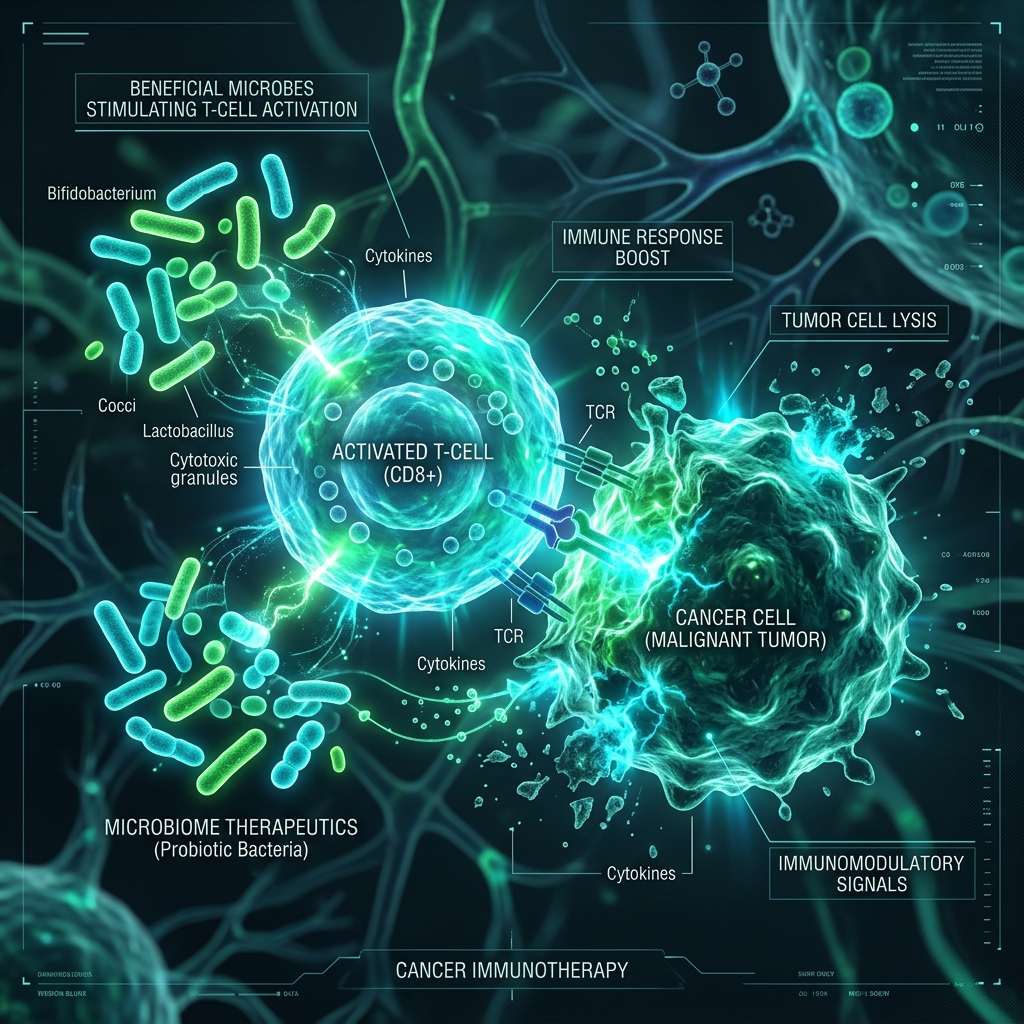
  • Targeted PD-L1 Binding: Fc-engineered humanized IgG1 monoclonal antibody that selectively binds to PD-L1, preventing its interactions with both PD-1 and B7.1 (CD80) receptors on T-cells. This reactivates suppressed tumor-infiltrating lymphocytes, restoring their cytotoxic immune response against malignant cells.
  • Preservation of PD-L2 Signaling: Unlike anti-PD-1 antibodies that block both PD-L1 and PD-L2, atezolizumab selectively targets PD-L1, allowing PD-L2 to interact freely with PD-1. This preservation is hypothesized to maintain immune homeostasis in normal pulmonary and mucosal tissues, potentially modulating the risk of autoimmune toxicities.
  • Fc-Engineering (Aglycosylation): The Fc region is engineered with an asparagine-to-alanine mutation (N298A) to eliminate Fc-gamma receptor binding, preventing antibody-dependent cellular cytotoxicity (ADCC) against PD-L1-expressing effector T-cells.

Pivotal Clinical Trial Milestones Across Multiple Tumors

Atezolizumab's clinical efficacy spans major Phase 3 clinical benchmarks:

  • IMpower133 (Extensive-Stage Small Cell Lung Cancer): Established the first new standard of care in over twenty years by demonstrating that adding atezolizumab to carboplatin and etoposide significantly prolongs overall survival and progression-free survival in frontline ES-SCLC.
  • IMpower010 (Adjuvant NSCLC): Demonstrated significant disease-free survival (DFS) improvement in patients with resected Stage II–IIIA NSCLC whose tumors express PD-L1 (TC ≥1%), establishing atezolizumab as an adjuvant immunotherapy standard following platinum-based chemotherapy.
  • IMbrave150 (Unresectable Hepatocellular Carcinoma): The combination of atezolizumab and bevacizumab demonstrated superior overall survival and progression-free survival compared to sorafenib, establishing the new global frontline standard in advanced liver cancer.

Infusion Dosing Protocols & Flexible Scheduling

Tecentriq offers oncologists versatile administration schedules:

  • Dosing Options: Administered as an intravenous infusion at 1200 mg every 3 weeks, 840 mg every 2 weeks, or 1680 mg every 4 weeks. Initial infusion is given over 60 minutes; subsequent infusions can be administered over 30 minutes if tolerated.
  • Storage & Handling: Store in refrigerator at 2°C to 8°C in original carton to protect from light. Do not freeze or shake. Dilute in 0.9% Sodium Chloride Injection prior to administration; use an IV line containing a sterile, non-pyrogenic, low-protein-binding in-line filter (0.2–0.22 micron).

Immune-Mediated Adverse Reactions (irAE) Clinical Protocols

Proactive toxicity management ensures patient safety throughout immunotherapy:

  • Pneumonitis Surveillance: Patients should be monitored for signs of pneumonitis (cough, shortness of breath). Grade 2 pneumonitis requires withholding therapy and administering systemic corticosteroids (1–2 mg/kg/day prednisone); Grade 3 or 4 necessitates permanent discontinuation.
  • Endocrine & Hepatic Monitoring: Regular monitoring of liver function tests (AST, ALT, total bilirubin) and thyroid function (TSH, free T4) at baseline and before each infusion cycle.

Global Cold-Chain Sourcing via Critical Kare Pharma

Specialty cancer clinics, hospital pharmacies, and named patients worldwide rely on Critical Kare Pharma for compliant cross-border procurement of genuine Tecentriq 1200mg:

  • Compliant Regulatory Clearances: Facilitated under US FDA Personal Importation Policy (PIP), UK MHRA Named-Patient Import, Australian TGA Special Access Scheme (SAS), Brazilian ANVISA RDC import exemptions, and Middle East MOHAP authorizations.
  • Uncompromising Cold-Chain (2°C–8°C): Shipped in validated thermal packaging with continuous digital temperature data loggers to ensure biological integrity from dispatch to clinic receipt.
  • Full Batch Authentication: Supplied in original tamper-evident manufacturer cartons accompanied by official batch test reports and Certificates of Analysis.

Contact our precision oncology desk for institutional procurement, batch availability, and express international shipping options: support@Critical Kare Pharma.com or connect directly with our oncology pharmacists via WhatsApp (+91 94275 19809).
Immunotherapy

Tecentriq Atezolizumab 1200mg Cancer Immunotherapy Clinical Review and Global Sourcing Guide 2026

C
Critical Kare PharmaImmuno-Oncology Desk
October 1, 2026—
Tecentriq Atezolizumab 1200mg Cancer Immunotherapy Clinical Review and Global Sourcing Guide 2026
Critical Kare

At a glance

Evidence-informed overview from Critical Kare Pharma. Key themes in this article:

  • Clinically reviewed framing
  • Safety & protocol awareness
  • Patient-relevant takeaways

Prefer to chat on WhatsApp?

Message our pharmacy team directly about this treatment — we reply with product details, sourcing, and next steps.

Chat on WhatsApp

On October 1, 2026, thoracic and uro-oncology symposiums reiterated the clinical significance of Tecentriq® (Atezolizumab 1200 mg / 20 mL and 840 mg / 14 mL concentrate for solution for infusion) developed by Genentech / Roche. As the first engineered monoclonal antibody targeting programmed death-ligand 1 (PD-L1), Tecentriq reverses T-cell exhaustion while leaving PD-L2 intact, anchoring cornerstone regimens in Extensive-Stage Small Cell Lung Cancer (ES-SCLC), adjuvant non-small cell lung cancer (NSCLC), metastatic urothelial carcinoma, and unresectable hepatocellular carcinoma (HCC).

Through Critical Kare Pharma, verified authentic Genentech / Roche packs of Tecentriq Atezolizumab 1200mg & 840mg Injection are accessible to oncology institutions, clinical research centers, and named patients globally via GDP-certified 2°C–8°C cold-chain logistics and validated Certificate of Analysis (COA) batch release.

Tecentriq Atezolizumab 1200mg vial in sterile oncology cleanroom with digital temperature monitor

Mechanism of Action: Selective PD-L1 Checkpoint Inhibition

Atezolizumab possesses unique molecular design features that differentiate it from other immune checkpoint inhibitors:

  • Targeted PD-L1 Binding: Fc-engineered humanized IgG1 monoclonal antibody that selectively binds to PD-L1, preventing its interactions with both PD-1 and B7.1 (CD80) receptors on T-cells. This reactivates suppressed tumor-infiltrating lymphocytes, restoring their cytotoxic immune response against malignant cells.
  • Preservation of PD-L2 Signaling: Unlike anti-PD-1 antibodies that block both PD-L1 and PD-L2, atezolizumab selectively targets PD-L1, allowing PD-L2 to interact freely with PD-1. This preservation is hypothesized to maintain immune homeostasis in normal pulmonary and mucosal tissues, potentially modulating the risk of autoimmune toxicities.
  • Fc-Engineering (Aglycosylation): The Fc region is engineered with an asparagine-to-alanine mutation (N298A) to eliminate Fc-gamma receptor binding, preventing antibody-dependent cellular cytotoxicity (ADCC) against PD-L1-expressing effector T-cells.

Pivotal Clinical Trial Milestones Across Multiple Tumors

Atezolizumab's clinical efficacy spans major Phase 3 clinical benchmarks:

  • IMpower133 (Extensive-Stage Small Cell Lung Cancer): Established the first new standard of care in over twenty years by demonstrating that adding atezolizumab to carboplatin and etoposide significantly prolongs overall survival and progression-free survival in frontline ES-SCLC.
  • IMpower010 (Adjuvant NSCLC): Demonstrated significant disease-free survival (DFS) improvement in patients with resected Stage II–IIIA NSCLC whose tumors express PD-L1 (TC ≥1%), establishing atezolizumab as an adjuvant immunotherapy standard following platinum-based chemotherapy.
  • IMbrave150 (Unresectable Hepatocellular Carcinoma): The combination of atezolizumab and bevacizumab demonstrated superior overall survival and progression-free survival compared to sorafenib, establishing the new global frontline standard in advanced liver cancer.

Infusion Dosing Protocols & Flexible Scheduling

Tecentriq offers oncologists versatile administration schedules:

  • Dosing Options: Administered as an intravenous infusion at 1200 mg every 3 weeks, 840 mg every 2 weeks, or 1680 mg every 4 weeks. Initial infusion is given over 60 minutes; subsequent infusions can be administered over 30 minutes if tolerated.
  • Storage & Handling: Store in refrigerator at 2°C to 8°C in original carton to protect from light. Do not freeze or shake. Dilute in 0.9% Sodium Chloride Injection prior to administration; use an IV line containing a sterile, non-pyrogenic, low-protein-binding in-line filter (0.2–0.22 micron).

Immune-Mediated Adverse Reactions (irAE) Clinical Protocols

Proactive toxicity management ensures patient safety throughout immunotherapy:

  • Pneumonitis Surveillance: Patients should be monitored for signs of pneumonitis (cough, shortness of breath). Grade 2 pneumonitis requires withholding therapy and administering systemic corticosteroids (1–2 mg/kg/day prednisone); Grade 3 or 4 necessitates permanent discontinuation.
  • Endocrine & Hepatic Monitoring: Regular monitoring of liver function tests (AST, ALT, total bilirubin) and thyroid function (TSH, free T4) at baseline and before each infusion cycle.

Global Cold-Chain Sourcing via Critical Kare Pharma

Specialty cancer clinics, hospital pharmacies, and named patients worldwide rely on Critical Kare Pharma for compliant cross-border procurement of genuine Tecentriq 1200mg:

  • Compliant Regulatory Clearances: Facilitated under US FDA Personal Importation Policy (PIP), UK MHRA Named-Patient Import, Australian TGA Special Access Scheme (SAS), Brazilian ANVISA RDC import exemptions, and Middle East MOHAP authorizations.
  • Uncompromising Cold-Chain (2°C–8°C): Shipped in validated thermal packaging with continuous digital temperature data loggers to ensure biological integrity from dispatch to clinic receipt.
  • Full Batch Authentication: Supplied in original tamper-evident manufacturer cartons accompanied by official batch test reports and Certificates of Analysis.

Contact our precision oncology desk for institutional procurement, batch availability, and express international shipping options: support@Critical Kare Pharma.com or connect directly with our oncology pharmacists via WhatsApp (+91 94275 19809).



C

Critical Kare PharmaImmuno-Oncology Desk

Specialists in programmed death-ligand 1 (PD-L1) checkpoint biology, non-small cell and extensive-stage small cell lung cancer regimens, and international named-patient biologic import.

Continue your care journey

This article is for general education. For medicine availability, prescriptions, and orders, use our catalog and pharmacy team.

Chat on WhatsAppBrowse catalogTreatmentsContact pharmacistsUpload prescription

Related Articles

Next Generation Oncolytic Viruses Expanding Cancer Immunotherapy Reach

Immunotherapy

Next Generation Oncolytic Viruses Expanding Cancer Immunotherapy Reach

Read Article

Found this helpful?